Helicobacter pylori infects roughly half the world's population, yet most people never learn they have it until it starts causing the stomach symptoms treatment is designed to resolve.
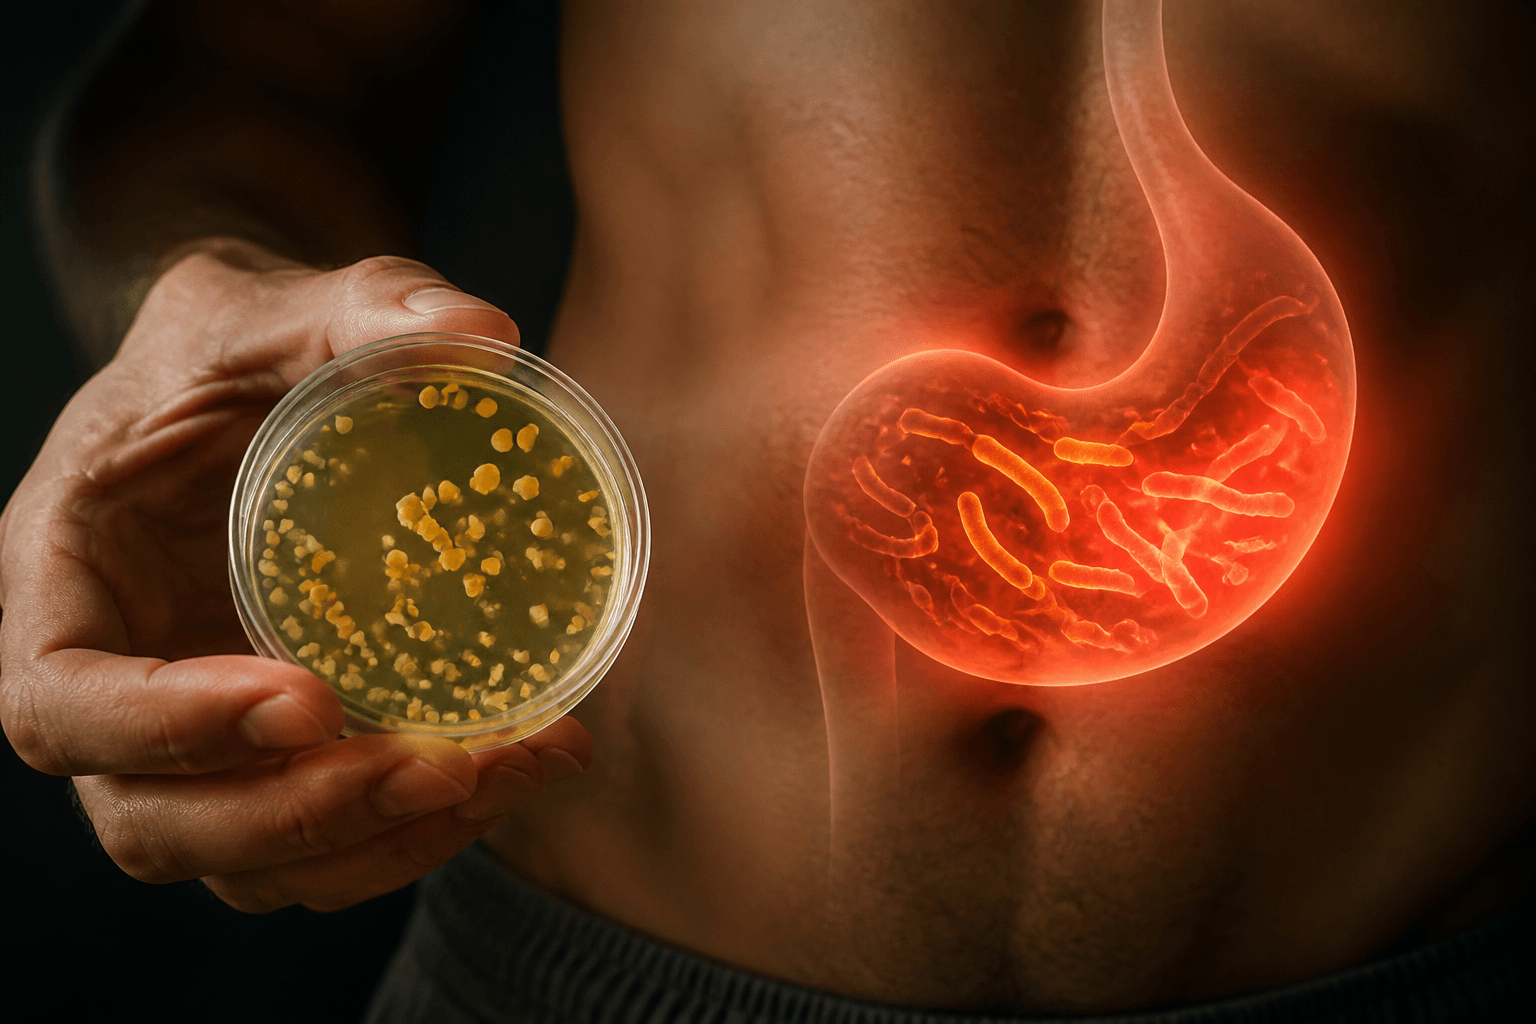
Helicobacter pylori is one of the most common chronic bacterial infections in the world, quietly colonizing the stomach lining of an estimated half of the global population, often for decades without producing a single symptom. What eventually brings it to medical attention — persistent indigestion, an ulcer, or an unexplained iron deficiency — is only the visible tip of a much longer, largely silent relationship between this bacterium and the stomach lining it has adapted specifically to survive in.
How a Bacterium Survives the Stomach's Acid
Most bacteria can't survive stomach acid, which is precisely why H. pylori is so biologically unusual: it produces an enzyme called urease that converts urea into ammonia, neutralizing acid in its immediate surroundings and creating a small protected pocket within the mucus layer lining the stomach wall. From that sheltered position, it can persist indefinitely unless specifically treated, gradually provoking a low-grade inflammatory response in the surrounding tissue that, over years, can lead to gastritis, ulcers, or in a small proportion of long-term carriers, an increased risk of stomach cancer.
Why Most Infections Stay Silent
The majority of people carrying H. pylori never develop noticeable symptoms, and researchers don't yet fully understand why the same bacterium causes significant disease in some people and remains harmless in others — factors likely include the specific strain involved, genetic differences in the host's inflammatory response, and other lifestyle factors such as diet and smoking. This variability is part of why testing is generally reserved for people with a specific reason to suspect infection, such as ongoing upper digestive symptoms, a diagnosed ulcer, or a family history of stomach cancer, rather than broad population-wide screening.
How the Infection Is Actually Diagnosed
Several reliable testing methods exist, each with different practical trade-offs. A urea breath test, which detects the byproducts of the bacterium's own urease enzyme, is non-invasive and widely used, as is a stool antigen test that directly detects H. pylori proteins in a stool sample. Blood antibody tests are less favored for confirming an active infection, since antibodies can remain detectable long after successful treatment, making them more useful for past-exposure screening than for confirming current infection. Endoscopy with a tissue biopsy is generally reserved for cases where a doctor already needs to examine the stomach lining directly for other reasons, such as investigating an ulcer.
Why Treatment Requires Multiple Medications at Once
Unlike many bacterial infections treated with a single antibiotic, H. pylori is generally treated with a combination of two antibiotics plus an acid-suppressing medication, typically a proton pump inhibitor such as omeprazole (Prilosec), taken together for one to two weeks. This combination approach exists because the bacterium has developed meaningful antibiotic resistance in many regions, and using a single antibiotic alone carries a substantially higher risk of treatment failure and further resistance developing. The acid-suppressing component isn't just for symptom comfort — reducing stomach acidity is thought to improve how effectively the antibiotics reach and act on the bacterium within its protected niche.
Important
Completing the full course of combination therapy exactly as prescribed, rather than stopping early once symptoms improve, is one of the most important factors in successful eradication, since an incomplete course is a leading cause of treatment failure and antibiotic resistance.
Confirming eradication with a follow-up breath or stool test, generally four or more weeks after finishing treatment and after stopping acid-suppressing medication for a period beforehand, is the only reliable way to know the infection has actually cleared.
What Happens When First-Line Treatment Fails
Treatment failure is common enough that doctors generally don't assume success without confirmatory testing. When first-line therapy doesn't clear the infection, a doctor will typically switch to a different combination of antibiotics rather than repeating the same regimen, since a failed course often indicates that the bacterial strain is resistant to one of the antibiotics used. In some cases, susceptibility testing on a biopsy sample can help identify which antibiotics the specific strain will actually respond to, allowing for a more targeted second attempt rather than further trial and error.
Why Treating Even Asymptomatic Infection Is Sometimes Recommended
Although many carriers never develop symptoms, current guidance in several situations still recommends treatment even in the absence of symptoms — for instance, in people with a family history of stomach cancer, those about to start long-term NSAID use, or those with unexplained iron-deficiency anemia. This reflects a shift in thinking: because H. pylori is a known contributor to a small but real long-term cancer risk and to certain other conditions, eradicating it when identified is generally considered worthwhile even without active symptoms, though this decision is made individually with a doctor rather than applied universally.